
Introduction
Pulmonary nodules are focal lesions smaller than 3 cm in diameter, which are detected in up to 30% of all chest computed tomography scans, frequently occurring as multiple lesions and becoming increasingly common in patients with a prior diagnosis of cancer.1 A percentage of these nodules in subjects with cancer are of indeterminate characteristics, with diverse etiologies, both benign and malignant.1 The survival of patients with cancer has shown progressive improvement in recent decades, allowing these individuals to live long enough to develop another neoplasm.2 Among the origins of this second neoplasm, lung cancer ranks among the foremost; this is associated with risk factors shared with the initial cancer.2
Regarding pulmonary nodules in subjects with confirmed extrathoracic malignancy, the literature emphatically considers this clinical characteristic a risk factor for the nodule being of malignant etiology; likewise, the size of the pulmonary lesion can guide the diagnosis of malignancy, with a cutoff point of nodules larger than 8.5 mm, in which a nodule of malignant origin is more likely, yet without characterizing the associated risk of having a new pulmonary neoplasm.3
The current problem is that the algorithms used for the management of pulmonary nodules exclude subjects with a prior diagnosis of malignancy. For example, Swensen in 1999 published a comparison between the Mayo Clinic predictive model and the clinical interpretation of pulmonary nodules, in which they methodologically excluded individuals with a history of cancer in the prior five years and a prior diagnosis of pulmonary cancer.4 The 2016 Fleischner Society guideline for pulmonary nodules specifically clarifies that it excludes subjects with a history of malignancy, so its extrapolation to an oncological population is limited.5 Finally, the American Journal of Roentgenology (AJR) published in 2021 a narrative review by an expert panel, which reports that the risk of malignancy of a pulmonary nodule in a subject with extrapulmonary cancer is very high (up to 80%), including metastases or de novo primary pulmonary tumors among these, and emphasizing the need for histopathological study in this clinical scenario and individualization of malignancy risk assessment.2 In the review of the literature, no validated model was found to discriminate metastatic lesions from de novo primary pulmonary tumors in individuals with a history of extrapulmonary cancer.
Therefore, the objective of this study was to describe the etiology of pulmonary nodules in subjects with diagnosed extrapulmonary cancer and to analyze the associations between the radiological and clinical findings of those with malignant etiology (de novo primary pulmonary tumors or metastases), with the aim of optimizing the oncological risk stratification of these lesions.
Method
The methodology and analysis flowchart is shown in figure 1.

Figure 1. Methodology and analysis flowchart.
Study design and population
A single-center, retrospective observational study was conducted, whose objective was to describe and analyze – in adults with extrapulmonary malignancies who, during the diagnosis or follow-up of their primary tumor, developed one or more pulmonary nodules – the sociodemographic variables, personal history, and clinical characteristics of the individuals, as well as the radiological findings and histopathological diagnosis of the nodules.
Data source and eligibility criteria
The data source was the database of the Department of Thoracic Surgery of the Instituto Nacional de Cancerología (Bogotá, Colombia). Individuals ≥ 18 years of age with a diagnosis of extrapulmonary malignancy were included if, during the workup of their primary tumor (diagnosis or follow-up), at least one pulmonary nodule was identified and underwent histopathological examination (considered the reference standard for establishing its etiology). The inclusion period covered the years 2018-2023. The following were excluded: pregnant women, subjects with a history of pulmonary cancer, calcified granulomas as the sole finding, and cases without availability of diagnostic images for review.
Variables studied and data collection
The sociodemographic variables (age, sex, place of birth, place of origin, and occupation), personal history (psychoactive substance use, smoking, and exposure to other toxins such as asbestos and/or silica), and clinical characteristics (oncological diagnosis of the primary tumor, TNM stage, time interval between tumors, treatment of the primary tumor, treatment discontinuation, type of treatment received, tumor recurrence, and mortality during nodule evaluation) were obtained from the institutional medical record.
Radiological evaluation
The radiological report of the first chest CT scan (multidetector CT with 1 mm slices and chest protocol) in which the pulmonary nodule was documented was reviewed, and the dominant nodule was identified, defined as the one that underwent histopathological examination by means of biopsy or surgical resection. From the report, the following variables were extracted: size, laterality, and lobar and segmental location of the nodule. Likewise, the radiological diagnostic impression was categorized into three groups: benign, malignant, or indeterminate. Subsequently, the images were subjected to a second reading by a radiologist with more than five years of experience in imaging studies for cancer, who was blinded to the original radiological report and completed the characterization of the dominant nodule (size, laterality, lobar and segmental location, relationship to the airway, shape, density/type, edges, and calcifications) and issued a new diagnostic conclusion, classified into the same three categories (benign, malignant, or indeterminate).
Histopathological evaluation
The histopathological report was reviewed, taking into account the macroscopy, microscopy, and immunohistochemistry corresponding to the dominant nodule, and according to this result, it was classified into three categories: de novo primary pulmonary tumor, metastasis, and benign tumor. For inferential analyses, histopathological malignancy was defined as the presence of metastasis or de novo primary pulmonary tumor.
Statistical analysis
R software (version 4.4.3) was used for all statistical analyses. Continuous variables were summarized using mean ± standard deviation (SD) or median (and interquartile range [IQR]), according to normality evaluated by the Shapiro-Wilk test; categorical variables were summarized using absolute and relative frequencies. To identify predictive factors for histopathological malignancy (defined as metastasis or de novo primary pulmonary tumor), a univariate and multivariate logistic regression model with a dichotomous outcome was fitted. Additionally, a multinomial logistic regression (nnet package) was implemented to evaluate predictors of the categorical dependent variable: histopathological diagnosis of the nodule (benign, metastasis, and de novo primary pulmonary tumor), with the reference category “benign.” Adjusted odds ratios (OR) and 95% confidence intervals (95% CI) were estimated as the measure of effect. The selection of covariates in the adjusted analysis combined the results of the bivariate analysis (statistical criterion) and clinical relevance. Goodness-of-fit was verified using Nagelkerke’s pseudo-R2 and the Hosmer-Lemeshow test (p > 0.05); multicollinearity was assessed using the variance inflation factor (VIF < 5).
Finally, agreement was evaluated using Cohen’s kappa index (κ), considering three comparisons: 1) radiological report vs. histopathology; 2) expert radiological review vs. histopathology; and 3) radiological report vs. expert radiological review. For these comparisons, the three-category classification (benign, malignant, or indeterminate) and the previously described histopathological classification were maintained.
Results
A total of 197 individuals were evaluated, with a median age of 65 years (IQR: 54-74 years), the majority being older than 65 years (50.8%), with a predominance of the female sex (59.9%). A total of 36.5% of subjects came from locations other than the capital of the country (Bogotá D.C.), 53.8% of them were actively employed at the time of pulmonary nodule diagnosis, and 27.9% of subjects had exposure to tobacco smoking (Table 1). A total of 95.9% of individuals had a solid organ tumor as their underlying diagnosis, the most common being those located in the lower digestive tract (18.5%), breast tumors (14.8%), and tumors of the female genital organs (9.5%) (Table 2 and Fig. 2).
Table 1. Sociodemographic characteristics
| Sociodemographic characteristics | n = 197 (%) | |
|---|---|---|
| Age (years) | Median (IQR) | 65.0 (54.0-74.0) |
| Sex, n (%) | Female | 118 (59.9) |
| Male | 79 (40.1) | |
| Origin | Bogotá | 125 (63.5) |
| Outside Bogotá | 72 (36.5) | |
| Currently employed† | Yes | 105 (53.8) |
| No | 91 (46.1) | |
| Exposure history*, n (%) | Yes | 85 (43.1) |
| No | 112 (56.9) | |
| Tobacco smoking, n (%) | Exposed | 55 (27.9) |
| Not exposed | 142 (72.1) | |
*Groups exposure to biomass smoke, asbestos, silica, and psychoactive substance use.
†At the time of pulmonary nodule diagnosis.
IQR: interquartile range.
Table 2. Clinical characteristics
| Clinical characteristics | n = 197 (%) | |
|---|---|---|
| Oncological diagnosis, n (%) | Solid | 189 (95.9) |
| Hematological | 8 (4.10) | |
| Location of primary tumor, n (%) | Abdomen | 48 (24.4) |
| Head and neck | 25 (12.7) | |
| Extremities and appendages | 40 (20.3) | |
| Pelvis | 31 (15.7) | |
| Thorax | 43 (21.8) | |
| Other | 10 (5.10) | |
| Staging, n (%) | Local involvement | 116 (58.9) |
| Locoregional involvement | 39 (19.8) | |
| Advanced disease | 33 (16.8) | |
| Not applicable | 9 (4.60) | |
| Active treatment, n (%) | Yes | 166 (84.3) |
| Chemotherapy | 61 (36.7) | |
| Chemotherapy + radiotherapy | 72 (43.4) | |
| Radiotherapy | 7 (4.22) | |
| Other* | 26 (15.7) | |
| No | 31 (15.7) | |
| Oncological diagnosis by organ, n (%) | Solid | 189 (95.9) |
| Breast tumors | 28 (14.8) | |
| Skin tumors | 15 (7.94) | |
| Tumors of the lip, oral cavity, and pharynx | 9 (4.76) | |
| Tumors of the endocrine glands | 16 (8.47) | |
| Tumors of the urinary tract and kidney | 13 (6.60) | |
| Tumors of the bones and cartilages | 11 (5.82) | |
| Tumors of the lower digestive organs | 35 (18.5) | |
| Tumors of the upper digestive organs | 10 (5.29) | |
| Tumors of the female genital organs | 18 (9.52) | |
| Tumors of the male genital organs | 13 (6.88) | |
| Tumors of indeterminate sites | 1 (0.53) | |
| Tumors of mesothelial and soft tissues | 14 (7.41) | |
| Tumors of respiratory and intrathoracic organs | 4 (2.12) | |
| Tumors of the eye, brain, and other CNS sites | 2 (1.06) | |
| Hematological | 8 (4.10) | |
| Gastric MALT lymphoma | 1 (12.5) | |
| Malignant tumors of lymphatic tissue, hematopoietic organs, and related tissues | 7 (87.5) | |
| Treatment discontinuation†, n (%) | Yes | 26 (13.2) |
| No | 171 (86.8) | |
| Time to diagnosis between pathologies (months) | Median in months (IQR) | 13.2 (2.00-39.0) |
| Time to diagnosis between pathologies (months) | < 6 6-12 ≥ 12 |
71 (36.0) 23 (11.7) 103 (52.3) |
| Tumor recurrence, n (%) | Yes | 58 (29.4) |
| No | 139 (70.6) | |
*Groups hormone therapy, immunotherapy, and targeted therapy.
†Oncological treatment of the extrapulmonary primary tumor.
IQR: interquartile range; CNS: central nervous system.
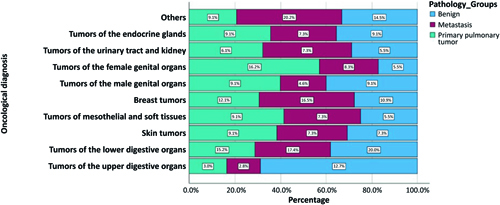
Figure 2. Etiology of the pulmonary nodule according to oncological diagnosis history.
Regarding the treatment received for the primary tumor at the time of nodule detection, 36.7% of individuals were receiving chemotherapy, 43.4% were receiving chemotherapy and radiotherapy, and 4.2% were receiving radiotherapy exclusively. A total of 13.2% had treatment discontinued during evaluation (not associated with it), 15.7% had no directed oncological treatment, and 29.4% had recurrence of the primary tumor. The time interval between the initial diagnosis of the primary tumor and the detection of the pulmonary nodule was calculated, finding a median of 13.2 months, with 52.3% of cases presenting after 1 year of follow-up (Table 2).
A total of 61.9% of pulmonary nodules were multiple, but the characteristics described below correspond to the dominant pulmonary nodule. Regarding size, the mean was 16.4 mm (SD: 11.5 mm); the majority were solid (88.8%), larger than 8 mm (80.7%), and their shape was described as indeterminate in 45.7% of cases; only 4.1% had calcifications, and their edges were predominantly smooth (32.5%) or lobulated (25.9%). Only 25 patients (12.7%) underwent 18F-fluorodeoxyglucose positron emission tomography/CT (18FDG-PET/CT) for the evaluation of the pulmonary nodule. In the initial radiology report, 45.2% of the nodules were reported as suggestive of being metastatic, 41.1% as indeterminate, and 4.1% as possible primary pulmonary tumors (Table 3).
Table 3. Radiological characteristics of pulmonary nodules
| Pulmonary nodule characteristic | n (%) |
|---|---|
| Multiple Single |
122 (61.9) 75 (38.1) |
| Laterality Right Left |
101 (51.3) 96 (48.7) |
| Lower lobe Upper lobe Middle lobe |
94 (47.7) 86 (43.7) 17 (8.6) |
| Peripheral Central |
147 (74.6) 50 (25.4) |
| Location Subpleural Perifissural Other location |
70 (35.5) 21 (10.7) 106 (53.8) |
| Density Solid Subsolid Partially solid Pure ground-glass |
175 (88.8) 22 (11.2) 18 (9.1) 4 (2.0) |
| Nodule shape Indeterminate Oval Round Triangular or polygonal |
90 (45.7) 57 (28.9) 48 (24.4) 2 (1.0) |
| Nodule edges Smooth Lobulated Irregular Spiculated |
64 (32.5) 51 (25.9) 48 (24.4) 34 (17.3) |
| Calcification pattern None Eccentric Punctate Central Diffuse |
189 (95.9) 2 (1.0) 2 (1.0) 2 (1.0) 2 (1.0) |
| Pleural tail No Yes |
171 (86.8) 26 (13.2) |
| Feeding vessel No Yes |
156 (79.2) 41 (20.8) |
| Pleural retraction No Yes |
176 (89.3) 21 (10.7) |
| Contrast enhancement No Yes |
144 (73.1) 53 (26.9) |
| Peripheral halo No Yes |
185 (93.9) 12 (6.1) |
| Cavitation No Yes |
182 (92.4) 15 (7.6) |
IQR: interquartile range.
The initial management of the analyzed pulmonary nodule consisted of direct surgical management in 53.8% of cases, biopsy (percutaneous or endoscopic) 16.2%, and surveillance in 30.0%, but all were ultimately referred for surgery or biopsy due to changes during follow-up. Of the patients taken to surgery, the most frequently performed procedure was pulmonary wedge resection (69.8%), followed by segmentectomy (20.8%). The histopathological diagnosis showed that there were 142 malignant pulmonary nodules (72.1%): 33 (16.8%) were de novo primary pulmonary tumors, and the remaining 109 were metastases (55.3%), while 53 nodules were secondary to benign etiologies (26.9%). Of the 75 patients with a single nodule, 16 (21.3%) were primary pulmonary tumors, 27 (36.0%) were metastases, and 32 (42.7%) were benign (Table 4).
Table 4. Histopathological characteristics of pulmonary nodules
| Biopsy characteristics | n (%) | |
|---|---|---|
| Surgery | 106 (53.8) | |
| Type of surgery | Wedge resection Segmentectomy Lobectomy |
74 (69.8) 22 (20.8) 10 (9.4) |
| Need for additional biopsy | Yes No |
0 (0) 106 (100) |
| Histopathological confirmation of nodule | Benign Primary pulmonary tumor Metastasis |
32 (30.2) 17 (16.0) 57 (53.8) |
| Non-surgical biopsy | 32 (16.2) | |
| Type of procedure | Image-guided percutaneous Bronchoscopy-guided transbronchial |
25 (78.2) 7 (21.8) |
| Histopathological confirmation of nodule | Yes No |
3 (9.38) 29 (90.6) |
| Benign Primary pulmonary tumor Metastasis |
11 (34.4) 3 (9.4) 18 (56.2) |
|
| Surveillance | 59 (30.0) | |
| Number of chest CTs performed | 2 3 ≥ 4 |
36 (61.0) 16 (27.1) 7 (11.9) |
| Time between 1st and 2nd chest CT* (days) | Median (IQR) | 95 (66.0-188.5) |
| Time between 2nd and 3rd chest CT† (days) | Median (IQR) | 116 (91.5-394.0) |
| Time between 1st and 3rd chest CT† (days) | Median (IQR) | 284 (194.8-711.0) |
| Change in management | Surgery Biopsy |
50 (84.6) 9 (15.2) |
| Histopathological confirmation of nodule | Benign Primary pulmonary tumor Metastasis |
10 (17.0) 12 (20.4) 34 (57.6) |
*n = 4 without CT at second follow-up.
†n = 41 without CT at second and third follow-up.
IQR: interquartile range; CT: computed tomography.
In the adjusted analysis using logistic regression with a dichotomous outcome, female sex (OR: 2.30; 95% CI: 1.01-5.20; p = 0.047), multiple nodules (OR: 3.06; 95% CI: 1.43-6.55; p = 0.004), lobulated edges of the pulmonary nodule (OR: 8.47; 95% CI: 2.17-33.08; p = 0.002), and a time interval of greater than 12 months between the diagnosis of the primary tumor and the detection of the pulmonary nodule (OR: 2.56; 95% CI: 1.09-6.02; p = 0.031) were associated with the etiology of malignancy (metastases or primary pulmonary tumors) (Fig. 3). On the other hand, through multinomial logistic regression analysis, an association was found between multiple nodules (OR: 3.88; 95% CI: 1.72-8.75; p < 0.01), lobulated edges of the pulmonary nodule (OR: 9.23; 95% CI: 2.20-38.6; p < 0.01), and a time interval between the diagnosis of the primary tumor and the detection of the pulmonary nodule greater than 12 months (OR: 2.82; 95% CI: 1.14-7.00; p = 0.025) with metastatic etiology. Meanwhile, an association was found between female sex (OR: 3.91; 95% CI: 1.21-12.7; p < 0.01), subsolid nodules (OR: 6.08; 95% CI: 1.25-29.6; p = 0.025), lobulated edges (OR: 6.77; 95% CI: 1.04-44.1; p = 0.045), and spiculated edges of the nodules (OR: 5.74; 95% CI: 1.03-32.1; p = 0.045) with primary pulmonary tumor etiology (Table 5).
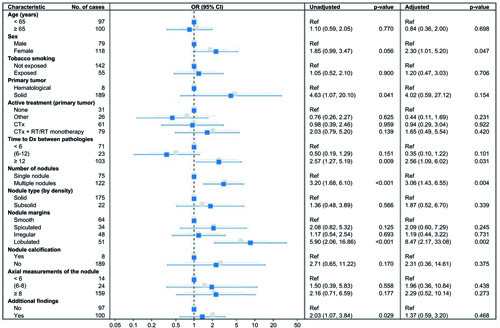
Figure 3. Forest plot: results of unadjusted and adjusted logistic regression analyses for risk factors associated with pulmonary nodule malignancy in patients with extrapulmonary malignant neoplasms (dichotomous outcome).
Table 5. Results of the multinomial logistic regression model for predictors of histopathological diagnosis in pulmonary nodules (benign, metastasis, or de novo primary tumor)
| Characteristic | Benign vs. metastasis | Benign vs. primary pulmonary tumor | ||
|---|---|---|---|---|
| OR (95% CI) | p | OR (95% CI) | p | |
| Age < 65 years ≥ 65 years |
Ref. 0.64 (0.26-1.59) |
0.30 |
Ref. 1.91 (0.56-6.58) |
0.30 |
| Sex Male Female |
Ref. 1.99 (0.84-4.74) |
0.12 |
Ref. 3.91 (1.21-12.7) |
< 0.01 |
| Tobacco smoking No Yes |
Ref. 1.09 (0.41-2.92) |
0.90 |
Ref. 1.46 (0.44-4.90) |
0.50 |
| Primary tumor Hematological Solid |
Ref. 6.67 (0.79-56.6) |
0.082 |
Ref. 1.37 (0.11-16.4) |
0.80 |
| Active treatment (primary tumor) None Other CTx CTx+RT/RT monotherapy |
Ref. 0.63 (0.14-2.74) 1.36 (0.38-4.85) 2.71 (0.72-10.1) |
0.50 0.60 0.14 |
Ref. 0.36 (0.06-2.12) 0.42 (0.09-1.95) 0.68 (0.15-3.08) |
0.30 0.30 0.60 |
| Time to diagnosis between primary tumor and nodule < 6 months 6-12 months ≥ 12 months |
Ref. 0.27 (0.07-1.10) 2.82 (1.14-7.00) |
0.068 0.025 |
Ref. 0.47 (0.09-2.50) 1.77 (0.54-5.75) |
0.40 0.30 |
| Number of nodules Single Multiple |
Ref. 3.88 (1.72-8.75) |
< 0.01 |
Ref. 1.74 (0.61-4.99) |
0.30 |
| Nodule type Solid Subsolid |
Ref. 0.87 (0.21-3.63) |
0.80 |
Ref. 6.08 (1.25-29.6) |
0.025 |
| Nodule edges Smooth Spiculated Irregular Lobulated |
Ref. 1.17 (0.31-4.39) 1.20 (0.42-3.44) 9.23 (2.20-38.6) |
0.80 0.70 < 0.01 |
Ref. 5.74 (1.03-32.1) 1.19 (0.22-6.34) 6.77 (1.04-44.1) |
0.047 0.80 0.045 |
| Nodule calcification Yes No |
Ref. 2.26 (0.33-15.5) |
0.40 |
Ref. NE |
|
| Nodule size < 6 mm 6-8 mm ≥ 8 mm |
Ref. 1.74 (0.28-10.7) 2.44 (0.51-11.7) |
0.50 0.30 |
Ref. 2.67 (0.15-47.9) 1.77 (0.13-24.8) |
0.50 0.70 |
| Additional findings on CT No Yes |
Ref. 1.34 (0.55-3.31) |
0.50 |
Ref. 1.35 (0.42-4.29) |
0.60 |
OR: odds ratio; CTx: chemotherapy; RT: radiotherapy; Ref.: reference value; CI: confidence interval; CTx: chemotherapy; RT: radiotherapy; Dx: diagnosis; NE: not estimable.
Finally, agreement was evaluated between the initial radiological report and review by an expert radiologist, contrasted with the histopathological report of malignant pulmonary nodules (metastases and primary pulmonary tumors). The agreement between the initial radiological report and the expert radiological review was only κ = 0.13 (95% CI: 0.002-0.26; p = 0.04); regarding the radiological report vs. the histopathological result, κ = 0.18 (95% CI: 0.06-0.30; p < 0.01), and the image review vs. histopathology, κ = 0.48 (95% CI: 0.35-0.61; p < 0.01), confirmed by the significance value (p) obtained (p < 0.05) that the calculated kappa value is significantly different from zero and that this agreement is not due to chance, being considered moderate according to the Landis and Koch (1977) classification.
Discussion
The management of pulmonary nodules in subjects with extrapulmonary cancer is not clearly defined, and guidelines such as the Fleischner Society guideline for incidental pulmonary nodules are not extrapolatable;5 their etiology can be benign or malignant, either through a primary pulmonary tumor or metastatic disease. Size remains a key determinant in pulmonary nodules, even in patients with a history of cancer, given that despite all the characteristics that can be described, it is an independent factor associated with malignancy.3 However, limitations currently exist regarding nodule measurements given their variability in measurement methodology and thus their predictive capacity in relation to neoplasms.6 In the evaluated population, a trend toward malignancy in pulmonary nodules larger than 8 mm was identified, but no statistical significance was found.
18FDG-PET/CT has proven to be a key tool in the diagnosis and staging of individuals with cancer that allows for deeper evaluation of pulmonary nodules, being a study that permits the reliable exclusion of malignancy.7 In this series, only 12.7% of patients underwent 18FDG-PET/CT for the evaluation of their pulmonary nodules, despite the fact that more than 80% of patients had nodules larger than 8 mm. This low utilization could be explained by administrative difficulties within the healthcare system,8 which delays clinical decision-making in this group of patients.
Regarding the initial approach of the evaluated individuals, it was identified that in 30% of cases initial imaging surveillance of the analyzed pulmonary nodule was chosen. Of these subjects, approximately 90% required at least three CT scans (including the initial one) with a median time interval between studies of 3-4 months before deciding to obtain a histopathological diagnosis. Notably, almost 80% of cases ultimately proved to be malignant lesions, underscoring the relevance of rigorous radiological follow-up and the complexity of the clinical decision involved.
The origin of pulmonary metastases is varied, but the literature describes some tumors that have a predilection for spreading to the lung, such as: sarcomas (36%), teratoma (37%), head and neck tumors (24%), and colon cancer (10%), among others.9 In this observation, the origin of metastases was predominantly from organs of the lower digestive tract (18.5%), followed by breast tumors (14.8%) and tumors of the female genital organs (9.5%).
There is an association between advanced tumor stages and the presence of pulmonary metastases; the series by Hong et al. showed that soft tissue sarcomas with higher histological grade or larger tumor size correlated with an increased risk of pulmonary dissemination.10 In this study, the majority of patients presented with tumors in early stages or with local involvement (58.9%); the discrepancy with the literature may be attributed to the heterogeneity of the population included in the cohort, where all types of neoplasms (including hematological ones) were included, reflecting the complexity of this clinical situation.
In the general population, it has been found that 10% of pulmonary nodules larger than 8 mm correspond to lung cancer, sharing risk factors with other neoplasms, such as tobacco smoking.11 In Colombia, a case series of breast cancer reported that 16.4% of resected pulmonary nodules corresponded to primary pulmonary tumors and that in 2% of subjects, metastatic pulmonary nodules and primary pulmonary tumors could coexist.12 In the United States, by 2006, cohorts already existed demonstrating a significant presence of primary pulmonary neoplasms in subjects with extrapulmonary cancer, associating non-calcified solid pulmonary nodules with primary pulmonary tumors (21.2%) more than with metastatic disease.13
On the other hand, subjects with extrapulmonary cancer, due to the disease itself and the immunosuppression derived from tumor-specific treatment, may develop inflammatory/infectious processes at the pulmonary level as the etiology of pulmonary nodules.14 When evaluating this problem, it is found that 75% of subjects may have nodules at the time of primary tumor diagnosis (measuring 2-49 mm) and 80% may be of benign etiology, especially those smaller than 10 mm or those with subpleural location.15,16 Even in high-grade soft tissue sarcomas, it has been reported that 39% of individuals had pulmonary nodules at the time of diagnosis and 69% corresponded to benign lesions.17 In this study, it was possible to identify that 26.9% of pulmonary nodules were benign despite the fact that clinical and imaging evaluation was suggestive of malignancy, but no specific radiological characteristics were found that would allow a malignant origin to be excluded.
In 2016, Caparica et al.18 published a single-center retrospective study in Brazil, including 228 patients with extrapulmonary malignancies who underwent percutaneous biopsy between 2011 and 2013, of whom 64.0% had metastases, 26.3% had a primary pulmonary tumor, and 9.6% had benign results. They found in the analysis that the presence of multiple pulmonary nodules (> 5 mm) (OR: 5.08; 95% CI: 2.62-9.84; p < 0.001) and cavitation or necrosis (OR: 2.90; 95% CI: 1.03-8.21; p = 0.04) were the two characteristics associated with a higher probability of metastatic disease. In this cohort, the predominant etiology of pulmonary nodules was metastatic (55.3%), while primary pulmonary tumors represented a smaller percentage (16.8%); an association between the presence of multiple pulmonary nodules and metastatic origin was also observed. In contrast, no relationship was found between cavitation and malignancy, which is related to its low frequency in the sample (only 7.6% of nodules were cavitated).
Similarly, Mery et al.19 analyzed 1,104 patients classified into three groups according to their oncological history. Our interest is focused on group 3 (n = 288 [26%]), corresponding to subjects with a history of extrapulmonary cancer. In this group, they described that 79% of these patients presented with malignant lesions, finding that subjects with breast or prostate tumors had a lower incidence of metastases and a higher frequency of primary pulmonary tumors. In contrast, the findings of this study showed that the greatest number of metastatic pulmonary nodules originated from tumors of the female genital tract, while the greatest number of primary pulmonary tumors was found in breast tumors. This divergence may reflect differences in regional patterns of cancer presentation and tumor biology across territories.
Additionally, Kokhar et al.,13 between 1999 and 2001 at Memorial Sloan-Kettering Cancer Center, included 151 patients with non-calcified pulmonary nodules from patients with extrapulmonary malignancies. In the univariate analysis, they found that nodule size, tobacco exposure, and single nodule were characteristics that increased the probability of malignancy, and in the multivariate analysis only size (OR: 1.07; 95% CI: 1.03-1.12; p = 0.001) and tobacco exposure (OR: 1.21; 95% CI: 1.05-1.38; p = 0.007) were predictive of malignancy. In our series, neither size nor tobacco exposure was a characteristic associated with malignancy in the logistic regression model; one possible reason may be the low number of patients who reported tobacco exposure in the cohort (27.9%).
Finally, Quint et al.,20 between 1994 and 1999, reviewed 149 medical records of patients with extrapulmonary malignancies who had a solitary pulmonary nodule. They found that smoking patients had a greater risk of the lesion being a primary pulmonary tumor rather than a metastasis (3.5 times greater risk). In our series, which included 75 patients (38.1%) with a single pulmonary nodule – 21.3% primary pulmonary and 36.0% metastases – no association was found in the combination of tobacco smoking and solitary pulmonary nodules.
Likewise, this study identified a greater risk of presenting metastatic pulmonary lesions in the female sex, which has not been evident in other series. This situation can be explained from the biological perspective of hormone-dependent tumors; estrogens play a determinant role in tumorigenesis and in the development of metastatic lesions due to their influence on stromal cell-derived factor (SDF-1α) and the proliferation of cancer-associated fibroblasts.21 There is also information regarding the relationship between the female sex and the possibility of pulmonary immunosuppression that leads to a favorable environment for tumor growth in this organ.22 Multiple pulmonary nodules have frequently been linked to metastatic disease; as in a series of colon cancer, the presence of multiple pulmonary nodules with irregular edges is a combination highly suggestive of metastases.23 In this series, one of the factors associated with pulmonary metastatic disease was the presence of multiple nodules. Nodule edges are an important characteristic when predicting malignancy, as demonstrated by studies in which subjects with extrapulmonary malignancies who had nodules with lobulated or smooth edges showed a direct association with metastatic disease.24 In this study, lobulated edges were found to correspond to a risk factor for malignancy.
Time intervals between the diagnosis of the primary tumor and the detection of pulmonary nodules can contribute to the diagnosis of malignancy; for melanomas, a probability of 94% of having metastases has been reported when these interval nodules appear in the first year of treatment.25 In this study, it was found that the presentation of a pulmonary nodule after 12 months was highly suggestive of metastatic disease. It is important to consider nodule density; subsolid nodules in subjects with extrapulmonary malignancies are frequently associated with primary pulmonary tumors or premalignant lesions, as described in 2008 by Park et al.26. In this study, a direct association was similarly found between subsolid pulmonary lesions and the diagnosis of primary pulmonary neoplasms.
Finally, the correlation between radiological findings and histopathological examination improved with expert review of the images; this result is consistent with that reported by Nordholm-Carstensen, who showed that review of images by thoracic radiologists improved the correlation between imaging diagnosis and histopathology (the reference method);27 a practice we consider essential when making a decision regarding the management of pulmonary nodules in patients with extrapulmonary malignancies.
Limitations
This study presents several limitations, including its retrospective, single-center design with a limited sample, as well as a low percentage of 18FDG-PET/CT utilization for the characterization of pulmonary nodules. Nevertheless, it stands out for its detailed description of the radiological characteristics of pulmonary nodules and the expert radiological review, providing robustness to the findings and offering relevant information for the evaluation and management of this clinical problem.
Conclusions
This study offers a comprehensive view of subjects with extrapulmonary malignancies who developed pulmonary nodules. Among the most relevant findings, factors associated with malignancy were identified, such as: female sex, multiple pulmonary nodules, lobulated nodule edges, and an interval greater than 12 months between the primary tumor diagnosis and the detection of the pulmonary nodule. This work highlights the value of expert radiological analysis, given that the review of images improved diagnostic agreement with pathological findings. The set of results obtained contributes significantly to the understanding of this clinical problem and lays the groundwork for future research.
Funding
No financial support or funding of any kind was received to carry out this research project.
Conflicts of interest
None of the authors report any conflict of interest in relation to the conduct of this study.
Ethical considerations
The study was conducted following the guidelines of the Declaration of Helsinki issued by the World Medical Association. In addition, the guidelines of Resolution 8430 of 1993 and Resolution 2378 of 2008 of the Ministry of Health of Colombia were followed, which establish the scientific, technical, and administrative norms for health research. This is a study that poses no ethical risks to the patients involved in its development due to its observational, descriptive, and retrospective characteristics, in which no intervention will be carried out. It was submitted and approved by the Ethics Committee of the Instituto Nacional de Cancerología in April 2024 through Act No. 0008-24.
Declaration on the use of artificial intelligence. None was used.
